Prev: Choosing wisely: the American College of Rheumatology's Top 5 list of things physicians and patients should questionNext: International recommendations for the assessment of autoantibodies to cellular antigens referred to as anti-nuclear antibodies

Record 006 · Clinical guidance · 2003
Diagnosis of Systemic Lupus Erythematosus
American Academy of Family Physicians · requested inclusion
“AAFP evidence-based review of SLE diagnosis reporting the ACR recommendation to order ANA only in patients with two or more unexplained organ-system signs, and the College of American Pathologists guideline on follow-up testing after a positive ANA.”
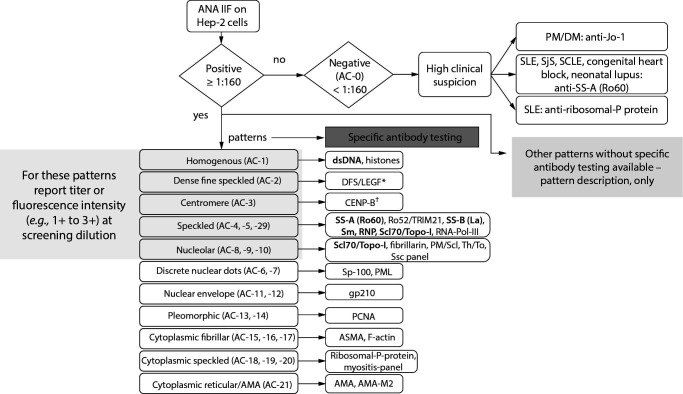
AAFP evidence-based review of SLE diagnosis reporting the ACR recommendation to order ANA only in patients with two or more unexplained organ-system signs, and the College of American Pathologists guideline on follow-up testing after a positive ANA. Candidate notes: ACR recommends ANA testing only in patients with two or more unexplained signs or symptoms; not indicated for isolated myalgias or arthralgias Persistently negative ANA (<1:40) can usually be assumed to rule out SLE; ANA was positive in 32% of the general population at 1:40 dilution but only 5% at 1:160 CAP guideline: if diagnostic criteria are met plus positive ANA, no further labs are needed; otherwise test anti-dsDNA and anti-Sm and do not test other autoantibodies Limits noted in the record: Dated 2003: predates the EULAR/ACR 2019 criteria and the ANA-as-entry-criterion framework Reports ACR/CAP guidance rather than generating original recommendations A positive ANA is not a diagnosis. Claims in this record are not verified.
A positive ANA is not a diagnosis. Claims in this record are not verified.
source
- follow-up-testing
- healthy-people
- interpretation
- negative-ana
- positive-ana
- systemic lupus erythematosus
Clinical guidance
Also in this file
View all in file Rheumatologic Tests: A Primer for Family Physicians18.08.X · American Academy of Family Physicians
 2019 European League Against Rheumatism/American College of Rheumatology classification criteria for systemic lupus erythematosus19.01.X · Annals of the Rheumatic Diseases / EULAR & ACR
 American College of Rheumatology: Five Things Physicians and Patients Should Question00.02.X · American College of Rheumatology
 Assessment of antinuclear antibodies (ANA): National recommendations on behalf of the Croatian society of medical biochemistry and laboratory medicine21.03.X · Biochemia Medica / Croatian Society of Medical Biochemistry and Laboratory Medicine