Prev: International recommendations for the assessment of autoantibodies to cellular antigens referred to as anti-nuclear antibodiesNext: Sjögren's Disease

Record 008 · Clinical guidance · 2018
Rheumatologic Tests: A Primer for Family Physicians
American Academy of Family Physicians · requested inclusion
“AAFP clinical review giving family physicians a framework for serologic testing in suspected connective tissue disease. It states ANA is the hallmark of SLE (present in >95% of SLE patients) but that most ANA-positive patients do not have SLE, and directs follow-up testing by suspected disease.”
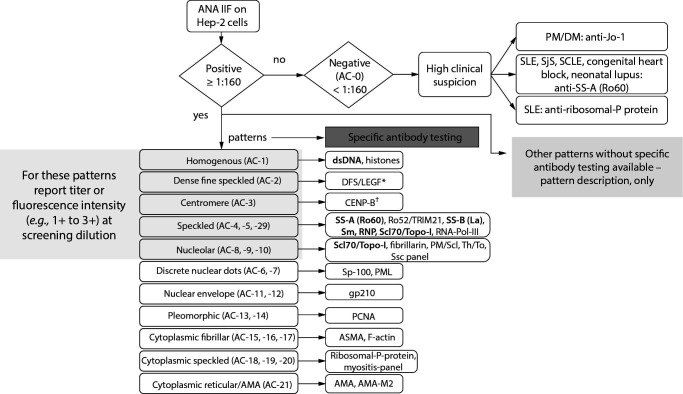
AAFP clinical review giving family physicians a framework for serologic testing in suspected connective tissue disease. It states ANA is the hallmark of SLE (present in >95% of SLE patients) but that most ANA-positive patients do not have SLE, and directs follow-up testing by suspected disease. Candidate notes: ANA by indirect immunofluorescence: sensitivity 93%, specificity 57% for SLE; by ELISA: sensitivity 81.9%, specificity 79.6% Once a patient has a positive ANA titer, it is rarely helpful to repeat the test; ANA levels fluctuate and do not reflect disease activity Pattern-disease associations: homogeneous or rim pattern in SLE; speckled in Sjogren syndrome; nucleolar in scleroderma; centromere pattern in limited scleroderma (CREST) Limits noted in the record: Primer-style review summarizing test characteristics from cited studies, not a formal systematic guideline with graded recommendations Reported test performance varies by assay manufacturer and patient population A positive ANA is not a diagnosis. Claims in this record are not verified.
A positive ANA is not a diagnosis. Claims in this record are not verified.
source
- follow-up-testing
- interpretation
- pattern
- positive-ana
- sjogren-syndrome
- systemic lupus erythematosus
- systemic sclerosis
- titer
Clinical guidance
Also in this file
View all in file Diagnosis of Systemic Lupus Erythematosus03.06.X · American Academy of Family Physicians
 2019 European League Against Rheumatism/American College of Rheumatology classification criteria for systemic lupus erythematosus19.01.X · Annals of the Rheumatic Diseases / EULAR & ACR
 American College of Rheumatology: Five Things Physicians and Patients Should Question00.02.X · American College of Rheumatology
 Assessment of antinuclear antibodies (ANA): National recommendations on behalf of the Croatian society of medical biochemistry and laboratory medicine21.03.X · Biochemia Medica / Croatian Society of Medical Biochemistry and Laboratory Medicine